

A vial of dried lizard venom ordered from a mail-order catalog in Utah would become the unlikely foundation for one of modern medicine’s most transformative drug discoveries.
What started as a seemingly absurd experiment in a Bronx VA hospital lab has evolved into a medication that treats diabetes, reverses obesity, prevents heart attacks, reduces addiction—and now appears to do something doctors have considered impossible for nearly three centuries.
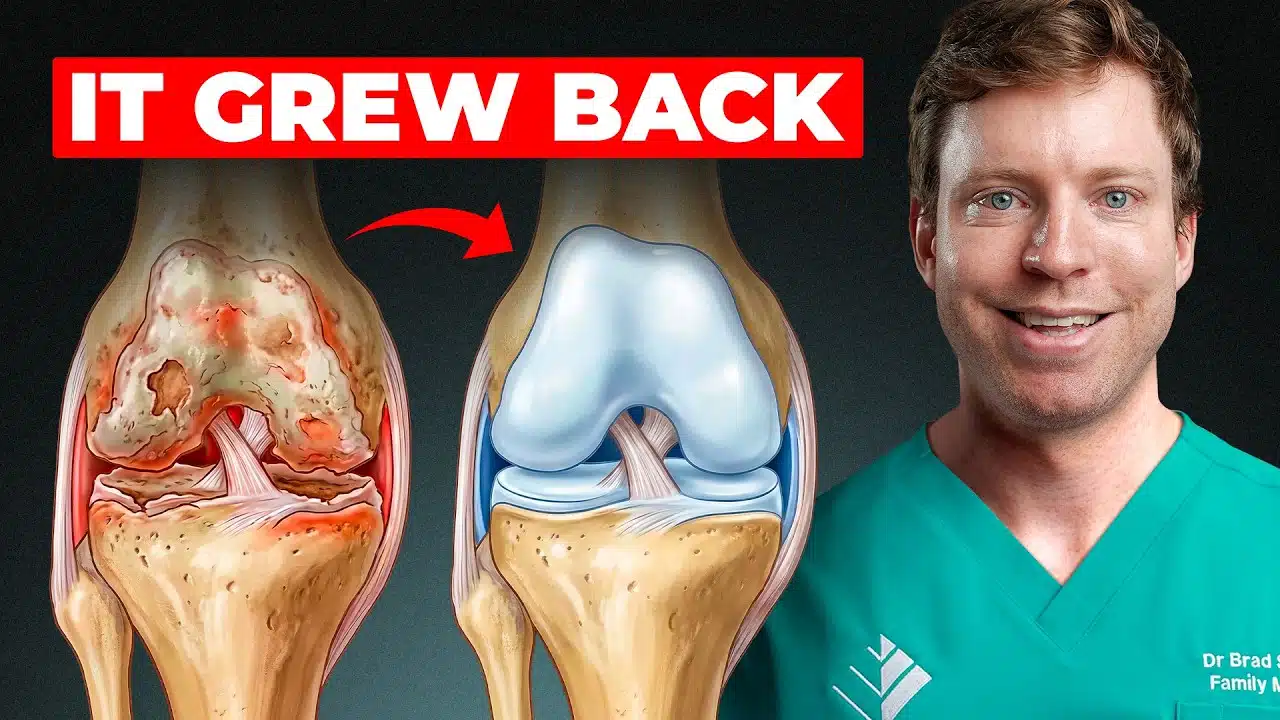
The compound derived from Gila monster venom is regenerating human cartilage.
That discovery challenges everything orthopedic medicine has believed since 1743.
Jump to:
From Desert Lizard to Medical Breakthrough
In the early 1990s, endocrinologist John Eng walked into his lab with an unconventional research subject. His colleagues thought he was wasting time studying Gila monster venom, one of only two venomous lizards on Earth.
But Eng had noticed something remarkable about these desert creatures. They eat as few as three times yearly, sometimes consuming up to a third of their body weight in a single meal—yet their blood sugar remains perfectly stable between feedings.
NIH researchers had already discovered that Gila monster venom affected the pancreas, the organ producing insulin. Researcher Jean-Pierre Ruffman described his work as “a fishing expedition that grant committees today would probably dismiss,” later admitting he’d “never conceived that there was any potential therapeutic benefit.”
Eng saw what others missed. Trained by Nobel Prize winner Rosalyn Yalow, he applied hormone-detection techniques to lizard venom and discovered exendin-4 in 1992—a compound 53% identical to human hormone GLP-1.
The Critical Difference That Changed Everything
Natural GLP-1 tells the pancreas to release insulin when blood sugar rises, but it breaks down within two minutes. Exendin-4 lasted hours in mice.
For someone with type 2 diabetes, this difference was potentially transformative. Eng had found a new way to treat one of Earth’s most common diseases.
Nobody wanted it.
Three Years of Rejection
Eng filed a patent in 1993, paying for it himself because the VA refused—it didn’t address veterinarian-specific ailments. He spent three years pitching pharmaceutical companies.
Peptide drugs had terrible reputations: expensive, difficult to manufacture, inconvenient for patients. A medication derived from lizard venom seemed absurd by industry standards.
In September 1996, Eng presented a poster at a diabetes conference in San Francisco. Researcher Andrew Young from Amylin Pharmaceuticals stopped to read it. One month later, Amylin licensed the patent.
Nine years later, in April 2005, the FDA approved Byetta—the first GLP-1 medication ever made, developed from a poster almost nobody stopped to look at.
The Surprising Cascade of Benefits
Byetta was modest. It required twice-daily injections, controlled blood sugar, and produced about 5% weight loss. Useful but unremarkable.
Eng’s discovery had proven something critical: targeting the GLP-1 receptor works. That proof opened doors for larger pharmaceutical companies to engineer more potent versions.
Novo Nordisk developed Victoza in 2010 (once-daily), then semaglutide—Ozempic—approved in 2017 (once-weekly). Each generation became more potent and longer-lasting.
Then the surprises started.
Weight Loss Nobody Expected
Patients on Ozempic were losing 15% of their body weight. The drug wasn’t designed for that. People were losing weight at rates previously only seen with bariatric surgery.
The FDA approved semaglutide specifically for obesity in 2021.
Heart Protection Beyond Weight Loss
The SELECT trial showed semaglutide reduced major cardiovascular events by 20% in people with obesity who didn’t have diabetes. Perhaps this was simply because patients lost weight—less strain on the heart.
That reasonable explanation became harder to sustain with the next set of findings.
Addiction Treatment Through Unexpected Pathways
A large VA study found patients on GLP-1 medications had significantly lower rates of substance abuse:
- 18% reduction in alcohol problems
- 20% reduction in nicotine use
- 25% reduction in opioid abuse
UAB neuroscientist Andrew Hardaway explained the mechanism:
Food simply becomes less rewarding. You still enjoy eating it, but it doesn’t drive behavior in the same way.
That same mechanism appeared to dampen brain reward responses to alcohol, nicotine, and opioids. This wasn’t just weight loss—it was something acting on the brain.
Kidney Protection Independent of Weight
The FLOW trial showed semaglutide reduced kidney disease risks and slowed disease progression. Benefits appeared even in patients who didn’t lose significant weight.
Researchers started finding GLP-1 receptors widely distributed across tissues: gut, pancreas, brain, heart, kidneys. Niles Kruger of Harvard Medical School captured researcher sentiment:
It’s just astounding how many indications these medications seem to be effective for or have some beneficial effects.
But even Kruger couldn’t have predicted what came next.
Challenging 283 Years of Medical Certainty
In 1743, Scottish surgeon William Hunter stood before the Royal Society in London and made a declaration that would define orthopedic medicine for three centuries: “When destroyed, it is never recovered.”
He was talking about cartilage. For 283 years, doctors have told patients with worn-out knees some version of the same thing.
Cartilage has no blood supply, no nerves—no efficient way to deliver nutrients cells need to grow new tissue. It’s one of few structures in the human body that, once damaged, has severely limited ability to repair itself.
Then patients on Ozempic started reporting something doctors initially dismissed: their joints felt better. Not just less pain from carrying less weight—something else, something unexpected.
The Obvious Explanation That Wasn’t Enough
Every kilogram lost removes roughly 4 kg of stress from knees. When Ozempic patients reported less joint pain, doctors shrugged. Of course knees hurt less after losing 30 pounds.
The STEP 9 trial, published in the New England Journal of Medicine in 2024, seemed to confirm this. After 68 weeks, pain scores dropped 42 points with semaglutide versus 28 with placebo. Patients lost 13.7% of body weight.
Case closed?
The Experiment That Changes Everything
Researchers at the Shenzhen Institutes of Advanced Technology weren’t satisfied with the weight-loss explanation. Led by Dr. Dai Chen, they designed an experiment to test it directly.
They took mice with osteoarthritis and split them into groups. One received semaglutide. The other was pair-fed—given restricted calories carefully controlled so they lost the same amount of weight as the semaglutide group.
Same weight loss, no drug. If joint improvements were just about weight loss, both groups should look identical.
They didn’t.
Same Weight Loss, Completely Different Outcomes
Pair-fed mice lost the same weight, but their cartilage kept deteriorating. Only the semaglutide group showed preserved cartilage, reduced inflammation, and fewer bone spurs.
Dr. Dai Chen explained the implications:
This controlled experiment demonstrates that semaglutide’s protective effect on cartilage in osteoarthritis is independent of weight loss, challenging the traditional belief that osteoarthritis improvement relies solely on weight reduction.
The Cellular Energy Switch
Here’s the simplest way to understand what’s happening. Cartilage cells—chondrocytes—need energy to maintain and repair surrounding tissue. In osteoarthritis, those cells get stuck running on an inefficient fuel source, like a factory running on a sputtering generator.
Barely enough energy to keep lights on, not nearly enough to rebuild anything.
Semaglutide flips a switch inside those cells, upgrading them to a clean, efficient energy source producing dramatically more power—enough to actually start repair processes.
Technically: GLP-1 receptors on cartilage cells (receptors nobody expected to find there) activate AMPK PFKFB3 signaling, shifting cells from glycolysis to oxidative phosphorylation. That triggers cells to start rebuilding tissue around them.
Evidence in Humans
Mouse cartilage isn’t human cartilage. Chen’s team ran a pilot clinical study: 20 patients aged 50 to 75, all with obesity and knee arthritis.
Half received standard treatment with hyaluronic acid injections. The other half received hyaluronic acid plus weekly semaglutide.
After 24 weeks, MRI scans revealed the semaglutide group showed an average 17% increase in cartilage thickness, suggesting regeneration. Control group: less than 1%.
Patients also experienced reduced pain and improved joint function.
The tissue William Hunter said “is never recovered,” that every orthopedic textbook says is irreplaceable, appears to be growing back.
Important Limitations
This was a pilot study of 20 patients over 24 weeks. Much larger and longer trials are needed. Study authors themselves wrote:
The protective effects of semaglutide on the human knee joint should be interpreted with caution and require further validation.
But the pair-fed mouse experiment makes this more than just another small study. It doesn’t just show correlation—it demonstrates a mechanism working independently of weight loss, consistent with broader patterns emerging with this drug class.
GLP-1 receptors keep turning up in places nobody expected, doing things nobody predicted.
What This Means for Osteoarthritis Treatment
These findings open possibilities for a radically new approach to osteoarthritis. We already know weight loss reduces pain, but we might now be able to actually regenerate cartilage.
There’s something else many people find surprising about addressing knee arthritis: exercise helps. We no longer think of osteoarthritis as just wear and tear.
The evidence shows specific exercises can reduce symptoms and improve function, working synergistically with emerging treatments to address both pain and underlying tissue damage.










